The doctor determines the method and duration after examination, review of your records and assessment of the extent of treatment.
Admission and discharge
The need for admission and timing of discharge depend on the method, anaesthesia and your general health. Obtain a plan from the medical centre before travelling.
Initial care and recovery
Allow time for rest, care of the treated area and help after discharge. You will receive instructions specific to the procedure.
Visits and follow-up
Arrange the next examination and, when necessary, removal of sutures or dressings with the clinical team. Your return journey should fit this plan.
Return to activity
Work, exercise and travel depend on healing and medical clearance; there is no single timetable for everyone.
About TAVI aortic valve replacement
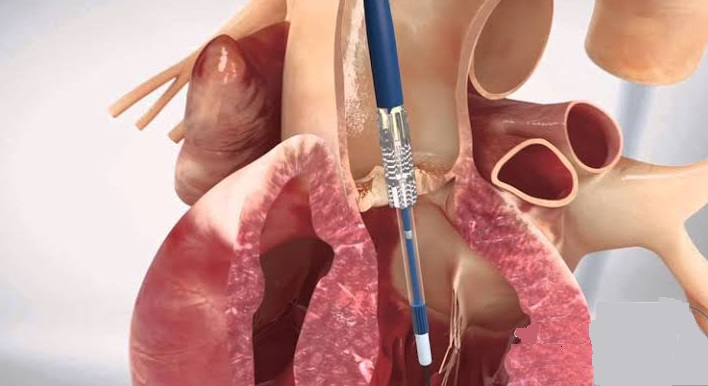
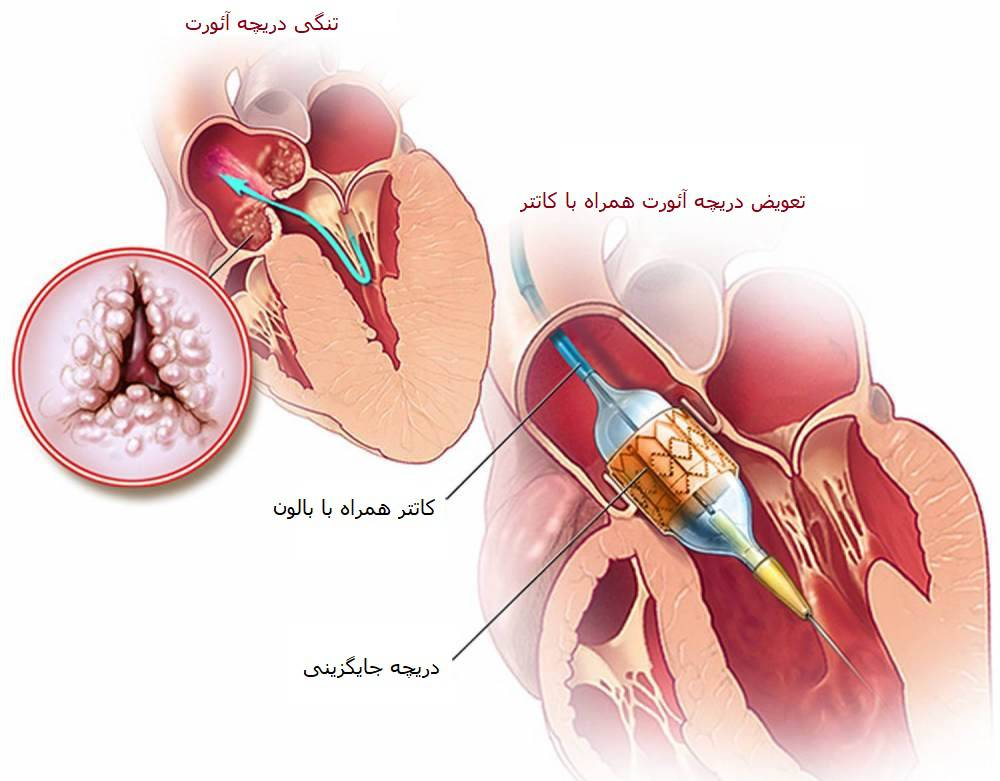
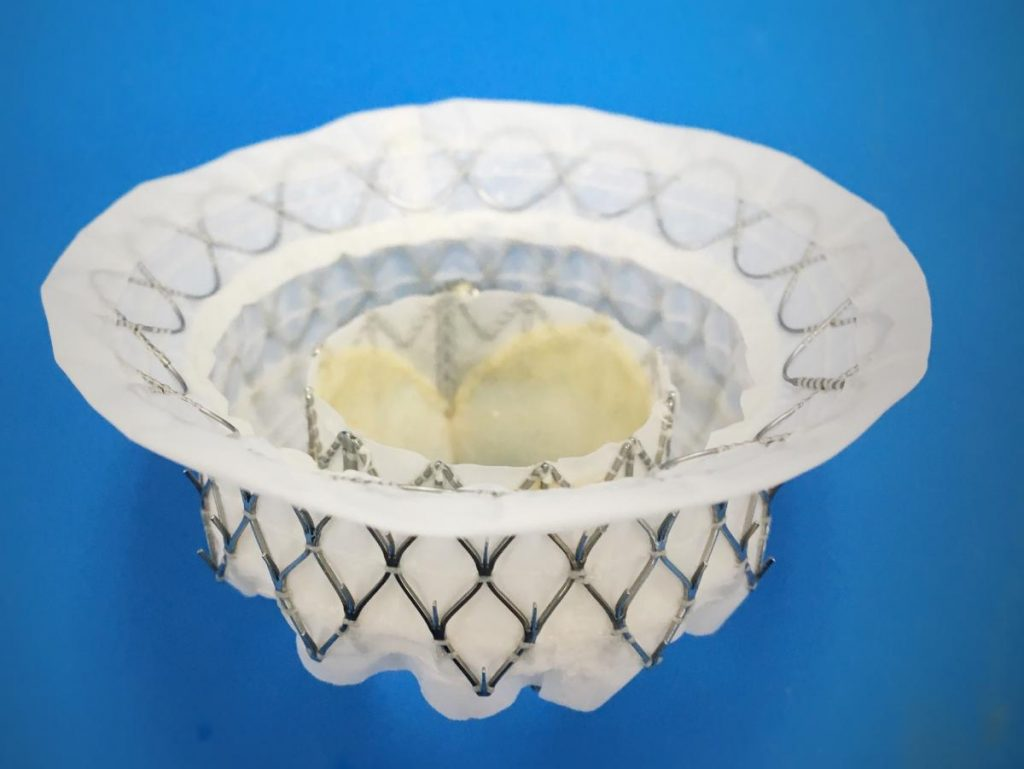
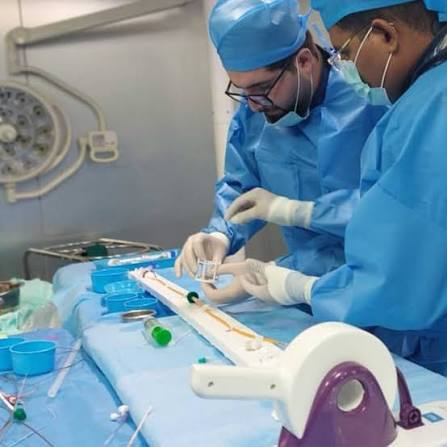
TAVI places a new aortic valve using a catheter, usually through a blood vessel in the groin. Other access routes may be considered according to anatomy. It can avoid a conventional open-chest operation in suitable patients, but eligibility, risks and long-term planning must be assessed by the heart team.
When tavi aortic valve replacement may be considered
TAVI is considered for severe aortic valve stenosis. The heart team assesses symptoms, severity, general health, valve and vessel anatomy and the option of surgical replacement. Procedure duration and local anaesthesia, sedation or general anaesthesia depend on the treatment plan.
Preparation and aftercare
Before treatment
The heart team may arrange CT imaging to assess the valve and access vessels.
Echocardiography assesses heart and valve function and the severity of aortic stenosis.
Blood tests may assess kidney function, clotting and haemoglobin.
Provide all medicines and underlying conditions. The team sets any dose changes or medication pauses; do not change medicines independently.
Discuss the procedure, expected course and any concerns before treatment.
After treatment
Care for the catheter entry site as instructed and avoid pressure or strain until allowed.
Walk and return to work or activity according to the heart team’s plan; feeling better is not clearance for strenuous exercise.
Take and adjust prescribed medicines, especially antithrombotic treatment, only as directed.
Attend reviews and echocardiograms. Discuss oral hygiene and dental procedures with the team.
Follow diet, smoking cessation and individual restrictions.
Report increasing bleeding or swelling at the access site, fever or feeling unwell. Chest pain, severe breathlessness or stroke symptoms require emergency help.
Recovery and follow-up
Recovery and review
Recovery is often shorter than after open surgery, but age, other illnesses, catheter access and complications affect the course. The heart team sets activity, medicines and follow-up after discharge.
Why coordinate with Medisa Medtour?
Treatment and travel are coordinated around your circumstances and the agreed care plan.
Review before travel
Your records and expectations are collected to arrange a specialist consultation. Requests for further information are followed up before travel.
Doctor and hospital coordination
Consultations and visits are arranged according to the doctor’s and medical centre’s schedules.
Help with communication
Interpreter and travel support can be coordinated to assist communication with your doctor and medical centre.
Follow-up coordination
Post-treatment visits and online follow-up, when available, are considered in accordance with the doctor’s plan.
Before travelling, check insurance coverage, exclusions and approval requirements with your insurer in your country of residence.
Support from Medisa Medtour
Online medical consultation before travelling to Iran
Interpreter coordination from arrival
Airport and treatment-related city transfers
Accommodation coordination
Specialist or subspecialist assessment after arrival
Coordination of required diagnostic and laboratory services
Coordination of treatment, necessary admission and agreed support for one companion
Online follow-up after treatment when arranged with the clinical team
Image gallery
Start with a consultation
Contact the Medisa team to discuss your request and arrange an initial consultation.
How does TAVI differ from surgical valve replacement?
Both replace a valve, but access and suitability differ. This is a general comparison and does not determine the right treatment for an individual.
Topic
TAVI
SAVR
Access
Usually a catheter through a blood vessel; the route depends on anatomy.
Surgical access to the heart; the incision depends on the technique.
Anaesthesia
Local anaesthesia with sedation or general anaesthesia, according to the plan.
Usually general anaesthesia.
Duration
Depends on access and the patient’s condition.
Depends on surgical extent and any additional procedures.
Admission
May be shorter in selected patients; discharge follows assessment.
A longer admission and care period may be needed.
Recovery
Often faster in suitable patients, with individual timing.
Healing of the incision and, when divided, breastbone contributes to recovery.
Scars
Catheter entry site or a limited incision depending on access.
A surgical incision appropriate to the method.
Valve choice
The implantable valve and long-term plan need review.
Choice depends on age, health and the treatment plan.
Patient selection
Age alone is insufficient; anatomy and heart-team assessment matter.
Age, surgical risk, valve durability and other treatment needs are considered.
What are the possible advantages of TAVI?
For a suitable patient, TAVI may mean a smaller incision and shorter admission or recovery. It still carries risks including bleeding, vascular injury, stroke, infection and a possible need for a pacemaker. Benefits and risks must be compared for that individual.
How long does a TAVI valve last?
Durability depends on the valve, age, other conditions and follow-up. No fixed lifespan applies to everyone. Discuss future intervention and valve-monitoring plans before choosing treatment.
What tests are needed before TAVI?
The team selects echocardiography, vascular imaging and blood tests to assess the valve, access, kidneys and blood status. Provide your medicines and underlying conditions.
What follow-up is needed after TAVI?
Catheter-site care, correct medicines, appropriate activity, oral hygiene and regular reviews matter. Ask about travel and activity restrictions, and report new problems promptly.